
How to perform the Supine Roll test
What is the supine roll test?
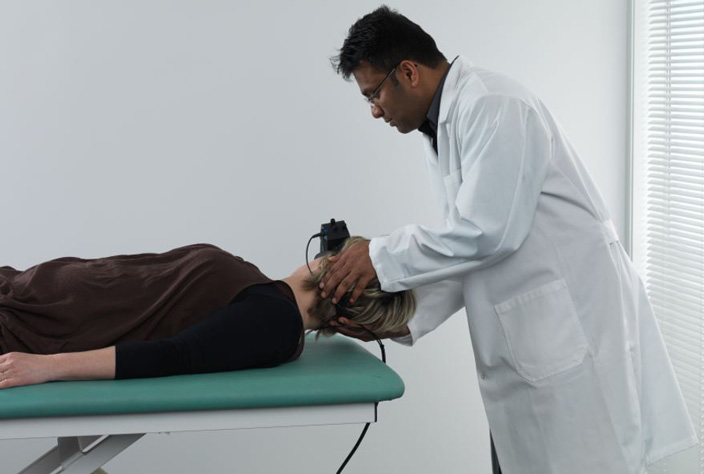
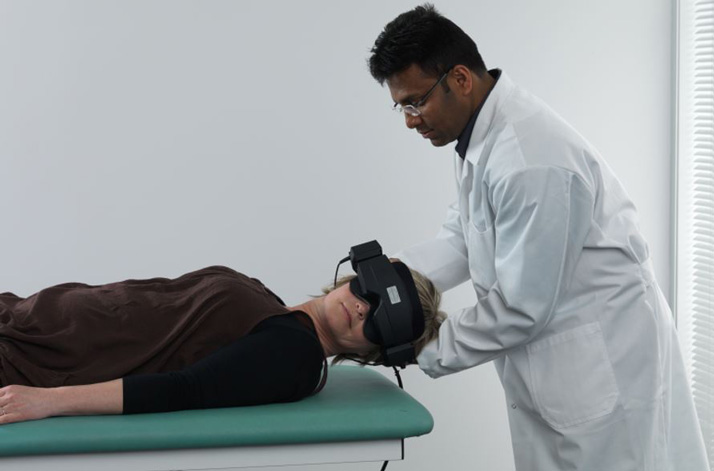
The supine roll test is a diagnostic maneuver used to identify horizontal canal benign paroxysmal positional vertigo (HC-BPPV). During the supine roll test, the patient lies down on their back and then turns their head 90 degrees to one side while keeping their eyes open. This maneuver is then repeated for the other side (Figures 1 and 2). If the patient experiences an episode of vertigo or nystagmus, this suggests the presence of HC-BPPV.
Pre-test considerations
Observe the following before performing the supine roll test.
1. Past injuries
Find out whether the patient has current or past injuries of the neck or spine.
2. Neurological symptoms
If neurological symptoms occur, stop the procedure immediately and refer for a neurological evaluation. These symptoms might include:
- Confusion
- Numbness
- Blurred vision
- Weakness of the arms or legs
3. Otoconia displacement
The consistency of fluid inside the vestibular system is viscous. Thus, you should allow enough time within each of the positions for the otoconia to achieve maximum displacement. This condition may also be responsible for a delayed onset of nystagmus.
4. Consider using VNG
It's most helpful to use Frenzel lenses or VNG goggles when performing positional maneuvers. This reduces the ability of the patient to fixate during the procedure in an attempt to reduce the nystagmus. This will also allow you to see even very slight horizontal nystagmus.
5. Affected ear
It's common for the patient to tell you during the intake interview which ear is affected and will describe accurately the symptoms of BPPV. Use this information to determine which ear is likely the affected. Always test both ears - even if the patient complains of only one side being affected.
6. Severe dizziness
Patients are often very sensitive to horizontal canal BPPV, resulting in severe dizziness. If the patient reacts violently during the supine roll test, immediately turn the patient to the opposite side and perform a Lempert (BBQ) roll.
Test procedure
- Begin with the patient sitting length-wise on the examination table.
- Place the Frenzel/VNG goggles on the patient.
- Guide the patient into a supine position. A slight elevation of the head (approximately 20 degrees) is helpful.
- Have the patient turn their head 90 degrees to either side. If the patient does not have enough cervical flexibility to provide maximum otoconia displacement, have them roll onto their shoulder.
- Observe whether nystagmus is present. Make note of the severity and the direction of the nystagmus.
- Guide the patient back into a neutral, supine position.
- Turn the patient's head 90 degrees to the opposite side (roll onto the shoulder if necessary).
- Again observe whether there is nystagmus. If so, make note of the severity and direction of the nystagmus.
- Guide the patient back into a neutral, supine position.
The following video shows how to perform a supine roll test using the TRV Chair.
Results
If you observe nystagmus, then it's important to distinguish between geotropic and apogeotropic nystagmus for treatment purposes.
1. Geotropic nystagmus
Nystagmus is worse on the affected side and beats toward the ground. Best treated with the Lempert (BBQ) roll. Acceptable alternative treatments are the Gufoni maneuver and forced prolonged positioning.
2. Apogeotropic nystagmus
Nystagmus is worse on the unaffected side and beats away from the ground. Best treated by first converting the nystagmus to geotropic and then performing the Lempert (BBQ) roll. Acceptable alternative treatments are:
- Head thrust
- Gufoni maneuver
- Forced prolonged positioning
- Vannucchi-Asprella maneuver
Further reading
[1] Korres, Stavros; Balatsouras, Dimitrios G.; Kaberos, Antonis; Economou, Constantinos; Kandiloros, Dimitrios; Ferekidis, Eleftherios. Occurrence of Semicircular Canal Involvement in Benign Paroxysmal Positional Vertigo. Otology & Neurotology 23(6):926-932, 2002.
[2] Gans RE. Evaluating the Dizzy Patient: Establishing Clinical Pathways. Hearing Review 6(6):45-47, 1999.
[3] Fife TD. Recognition and management of horizontal canal benign positional vertigo. Am J Otol. 19(3):345-351, 1998.
Presenter